
background

Blog

7 Tips for Choosing Suture Anchor Ankle Implants

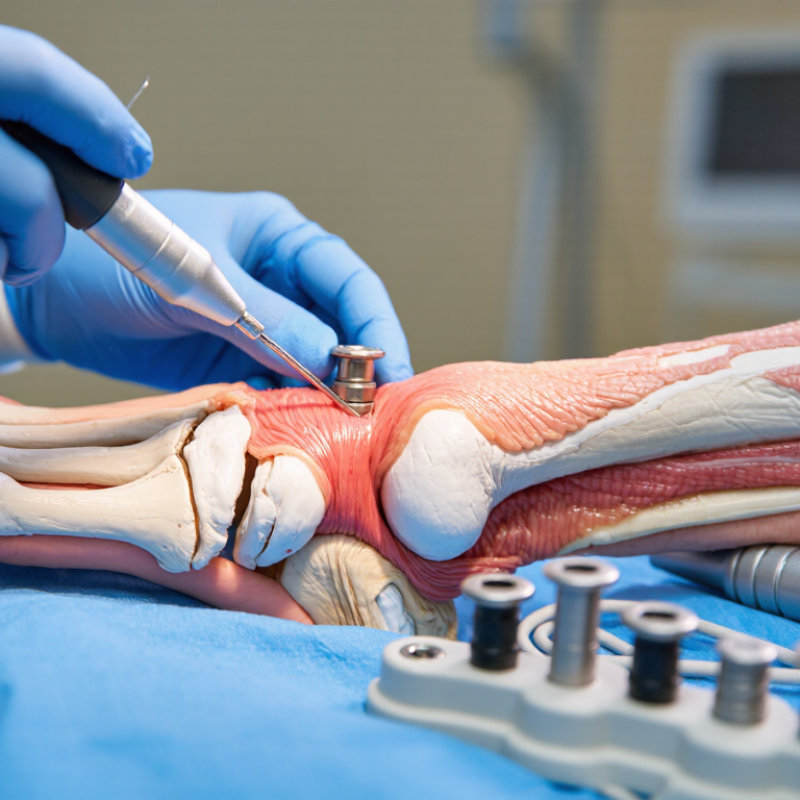
Choosing a Suture Anchor Ankle implant is a clinical decision, not a catalog exercise. Surgeons must weigh ligament quality, bone density, patient activity, fixation depth, and revision options. The anchor should fit the anatomy. Small details matter, such as insertion angle, drill size, and whether the knot sits beneath irritated soft tissue.

Recent reports from Grand View Research and Fortune Business Insights show continued growth in the global suture anchor market. Their findings reflect rising sports injuries, arthroscopic procedures, and demand for smaller fixation systems. However, these reports usually combine shoulder, hip, knee, and ankle applications. Ankle-specific conclusions require caution. That limitation deserves attention.

Foot-and-ankle specialist Dr. C. Thomas Haytmanek Jr. has stated, “The implant should support the repair, not replace sound surgical judgment.” This principle guides the seven tips in this article. Material selection, pullout strength, insertion control, radiographic visibility, and evidence-backed design all deserve careful comparison. A bioabsorbable anchor may reduce permanent hardware concerns, but its performance depends on bone healing and loading conditions. A metallic anchor can offer strong fixation, yet it may complicate imaging or revision surgery.

Real-world experience also exposes uncomfortable gaps. Laboratory strength does not always predict clinical success. Marketing language can sound more precise than the available evidence. Therefore, surgeons should review independent biomechanical studies, manufacturer instructions, post-market surveillance, and patient-specific risks before choosing a Suture Anchor Ankle system. The best choice is rarely the newest one. It is the one that provides reliable fixation, practical handling, and a defensible treatment rationale.
7 Tips for Choosing Suture Anchor Ankle Implants

Define the Ankle Injury and Its Suture Anchor Requirements

Define the ankle injury before choosing a suture anchor implant. A lateral ligament tear, syndesmotic disruption, and tendon injury require different fixation strategies. Review physical findings, stress tests, and imaging together. A small avulsion fragment may need a different anchor position than a soft-tissue tear. Bone quality matters too. Osteoporotic bone may offer less reliable purchase.

Tip: Match the anchor to the tissue and load. Consider anchor diameter, insertion depth, suture strength, and fixation angle. The implant should support the repair without creating unnecessary prominence near the joint. In practice, surgeons should also assess swelling, skin condition, and the patient’s activity demands. A competitive runner may require stronger protection than a sedentary patient, but healing still controls the timeline.

Tip: Define the repair’s practical requirements. Ask whether one anchor can restore the footprint or whether multiple points are needed. Check the drill path against nearby cartilage, tendons, and neurovascular structures. Keep the surgical plan clear.

Small details matter.

A checklist can miss them. For example, severe swelling may make landmarks less reliable on the day of surgery. Reassess when necessary. Implant selection should follow sound anatomy, current evidence, and the surgeon’s direct experience. No device replaces accurate diagnosis, careful placement, and patient-specific rehabilitation. Recovery plans should reflect fixation security, tissue biology, and the risk of early reinjury.

Compare Anchor Materials, Designs, and Biocompatibility

Choosing an ankle suture anchor requires more than comparing price or package size. Start with the material. Titanium offers strong fixation and familiar imaging behavior, while polymer options may reduce metal-related artifacts. Bioabsorbable materials can gradually disappear, but their degradation may cause swelling or cyst formation. The best choice depends on bone quality, repair tension, and follow-up plans.

Examine the anchor design closely. A broad thread may improve purchase in soft bone. A compact body can help in smaller ankle anatomy. Check insertion depth, driver control, and the risk of stripping during placement. Knotless designs can reduce surgical steps, yet they demand accurate tensioning. Suture diameter and abrasion resistance also matter. Small details become important under repeated loading.

Biocompatibility deserves evidence, not assumptions. Review peer-reviewed data on inflammatory response, migration, degradation, and revision procedures. Confirm that the implant fits the patient’s imaging needs, especially when future MRI assessment is likely. Surgeons should match the design with ligament location and rehabilitation demands. No anchor is perfect. A material that performs well in one repair may disappoint in weak bone. That uncertainty deserves discussion with the surgical team. Even experienced users should reassess handling, fixation strength, and tissue response after each case.

Assess Fixation Strength and Compatibility with Bone Quality

Choosing a suture anchor ankle implant starts with the patient’s bone, not the package description. Fixation strength must match the expected pullout forces. Consider anchor diameter, insertion depth, thread design, and material stiffness. A larger anchor is not automatically safer. It may weaken a small or fragile bone.

Bone quality changes with age, injury, disuse, and conditions affecting mineral density. Dense cortical bone can provide strong purchase near the surface. Soft cancellous bone may need deeper engagement or a different fixation strategy. Review imaging carefully, especially around the fibula, talus, and distal tibia. A narrow bony corridor leaves little room for error. Measure twice.

In practice, insertion torque offers useful feedback, but it should not be treated as a perfect strength test. Excessive torque can damage weak bone. Insufficient resistance may signal poor purchase, although technique and drill preparation can also influence it. Assess the implant’s compatibility with the planned suture, tissue load, and rehabilitation demands. The fixation should remain stable without creating unnecessary stress concentration. Small details matter.

Surgeons should also examine available clinical evidence, testing methods, and complication data. Laboratory pullout results may not represent every patient or loading pattern. That limitation deserves attention. A carefully selected anchor can still fail when bone quality is underestimated, placement is inaccurate, or rehabilitation progresses too quickly. Use a backup plan when fixation appears uncertain. Good judgment is often less dramatic than choosing the strongest implant.

7 Tips for Choosing Suture Anchor Ankle Implants

Assess fixation strength and compatibility with bone quality before selecting an implant.

The scores are an evidence-informed qualitative planning index, not direct measurements of pullout strength or a validated clinical score. Bone-quality terminology follows commonly used DXA T-score categories: normal, osteopenia, and osteoporosis.

1. Assess bone quality

Review DXA findings, radiographs, age, fracture history, and local bone conditions. Osteoporotic bone may require greater attention to fixation strategy.

2. Match the anchor to the anatomy

Choose an implant size and configuration that fit the available footprint while limiting risks to cartilage, tendons, nerves, and vessels.

3. Evaluate fixation strength

Consider insertion depth, thread design, cortical purchase, and resistance to cyclic loading rather than relying on size alone.

4. Check insertion angle

Follow the recommended trajectory and avoid excessive obliquity, which can reduce bone engagement and increase interface stress.

5. Consider material behavior

Compare permanent and resorbable materials for strength retention, imaging needs, tissue response, and the intended rehabilitation timeline.

6. Account for loading conditions

Ankle repairs may experience repeated tensile and shear forces. Match the construct to the repaired ligament, tendon, or capsule and expected activity.

7. Verify the full system

Confirm suture compatibility, deployment instruments, knot or knotless handling, backup fixation options, and the manufacturer’s instructions for use.

Review Surgical Technique, Delivery Systems, and Implant Placement

Choosing a suture anchor ankle implant starts with surgical technique, not packaging. A 2022 systematic review in Foot & Ankle International found that arthroscopic and open ligament repairs can provide comparable stability when patient selection and fixation are appropriate. The review also reported that complications remained clinically relevant, including nerve symptoms, stiffness, and anchor-related irritation. Technique still matters.

Delivery systems deserve close inspection. The inserter should provide a stable grip, clear depth markings, and controlled deployment through a small portal. A smooth suture path can reduce tangling around the cannula. It sounds minor. It is not. The American College of Surgeons NSQIP tracks 30-day complications across hundreds of hospitals, reminding surgeons that wound issues and readmissions deserve attention beyond the operating room. A well-designed system should support consistent handling, not encourage rushed placement.

Implant placement requires a firm grasp of anatomy. The anchor should sit in dense bone, avoid the joint surface, and follow the planned ligament footprint. Excessive tension can restrict motion, while shallow insertion may weaken fixation. Preoperative imaging helps identify bone quality and prior tunnels. I still think many surgical plans underestimate bone variation. The FDA’s MAUDE database is useful for detecting device-related signals, but it cannot establish complication rates. That limitation matters when comparing implants or interpreting marketing claims. Record insertion depth, fixation quality, and final ankle motion in the operative note. Those details improve later review.

7 Tips for Choosing Suture Anchor Ankle Implants - Review Surgical Technique, Delivery Systems, and Implant Placement
Tip Selection Dimension What to Review Practical Data and Considerations Clinical Checkpoint
1 Match the Anchor to the Indication Define the structure being repaired, the quality of the local bone, the expected load, and whether the repair is soft-tissue-to-bone or ligament-to-bone. Common ankle applications include lateral ligament repair or reconstruction, deltoid ligament repair, syndesmotic stabilization, Achilles-region procedures, and tendon or retinacular fixation. Small anchors are often considered for confined anatomy, while larger or stronger constructs may be selected when greater fixation strength is required. Confirm that the implant size and fixation method are appropriate for the target bone and do not interfere with nearby joints, tendons, nerves, or vessels.
2 Compare Implant Materials Evaluate whether a metallic, radiolucent polymer, or bioabsorbable implant is suitable for the procedure and the patient’s follow-up needs. Titanium and other metals provide durable fixation but can create imaging artifacts. PEEK and similar radiolucent polymers reduce metallic artifact. Bioabsorbable polymers are designed to gradually resorb, although the timing and local tissue response depend on the material and formulation. Review the potential for inflammatory response, cystic change, breakage, migration, or incomplete resorption where applicable. Material selection should not replace assessment of bone quality and construct stability.
3 Assess Suture Configuration Check the number of sutures, suture strength, strand configuration, eyelet design, and whether the system supports knot tying or knotless fixation. Knotless anchors can simplify tension management and reduce external knots. Knotted anchors may provide familiar control over tissue approximation. Braided high-strength sutures are commonly used for ligament and tendon fixation, but the final construct also depends on tissue quality, stitch pattern, and loading direction. Avoid excessive tension that can strangulate tissue or alter the intended ankle biomechanics. Ensure that the suture path does not abrade adjacent structures.
4 Review the Delivery System Examine the drill guide, punch or awl, drill bit, inserter, depth markings, handle design, and compatibility between the delivery instruments and the selected anchor. A guide can help control the entry point and trajectory, especially in small ankle bones. The system should permit controlled pilot-hole preparation, clear depth feedback, and reliable seating of the anchor without excessive force or instrument bending. Use the recommended instruments and sequence. Confirm that the guide is fully seated and that the pilot hole is not over-drilled, enlarged, or directed toward the articular surface.
5 Verify Surgical Technique Review exposure, tissue preparation, pilot-hole creation, anchor insertion, suture passage, tensioning, and final knot or locking steps. A typical workflow includes identifying the repair footprint, preparing only the necessary bone surface, placing the guide at the planned site, creating the pilot hole to the specified depth, inserting the anchor along the prepared trajectory, and securing the tissue with the planned stitch configuration. Preserve viable tissue and avoid unnecessary bone removal. If the pilot hole is compromised, do not force the same anchor into poor fixation; consider an approved alternative site or fixation strategy.
6 Plan Implant Placement Select the entry point, insertion angle, depth, and number of anchors according to the native footprint and the desired line of pull. Placement should recreate the anatomic origin or insertion as closely as practical while maintaining safe margins from the ankle, subtalar, and distal tibiofibular joints. Anchor orientation should support the expected load rather than simply follow the easiest access route. Avoid intra-articular penetration, cortical blowout, tendon obstruction, and conflict between multiple anchors. Confirm secure seating and stable tissue contact before closure.
7 Evaluate Evidence, Follow-Up, and Compatibility Review published clinical evidence, mechanical testing, instructions for use, imaging compatibility, postoperative protocols, and the surgeon’s experience with the system. Useful documentation includes pullout or cyclic-loading data, indications and contraindications, recommended drill dimensions, insertion depth, MRI conditions, and rehabilitation guidance. No mechanical test result alone predicts clinical performance in every patient. Check patient-specific factors such as bone quality, infection risk, allergy or material sensitivity, revision status, and compliance with protected weight-bearing or rehabilitation instructions.
Selection should be based on the specific injury, anatomy, bone quality, surgeon experience, and the implant’s current instructions for use. Dimensions, loading limits, insertion steps, and imaging conditions vary by device design.

Evaluate Safety Evidence, Recovery Needs, and Long-Term Performance

Choosing a suture anchor ankle implant requires more than checking size and price. Review peer-reviewed safety evidence, reported failure rates, and follow-up periods. Short studies can look reassuring. Long-term data matters more. Examine pullout strength, migration reports, inflammatory reactions, and revision rates. Evidence should reflect ankle procedures, not only laboratory testing or other joints.

Match the implant to bone quality, tendon loading, and the planned repair. A small anchor may suit limited tissue, while heavier repairs need stronger fixation. Material behavior also affects imaging, removal, and tissue response. Ask how the device performs during walking, stairs, and gradual return to sport. Recovery is not identical for every patient. Surgical technique, rehabilitation access, smoking status, and diabetes can change outcomes. Clear instructions are essential.

Look for transparent clinical data and independent complication reporting. Discuss expected pain, weight-bearing limits, wound care, and warning signs with the treating surgeon. Ask what happens if fixation loosens. Ask about revision options. Practical experience matters, but it can also introduce bias. No implant is risk-free. That deserves honest discussion. Long-term performance should include comfort, stability, repeat injury risk, and functional movement. A device that holds securely for six weeks may still disappoint years later. Some evidence remains incomplete, and that uncertainty should influence consent, follow-up, and implant selection.